The consultation and history-taking
Đã giới thiệu| English | Ý nghĩa |
|---|---|
| presenting complaint | presenting complaint |
| history of presenting complaint | history of presenting complaint |
| systems review | systems review |
| red flag | A feature that suggests a dangerous cause: a sudden "worst ever" headache with vomiting, chest pain with sweating, a new weakness, or weight loss with night sweats. |
Two minutes of listening
- A patient says, "It's my chest." A doctor who jumps in with "Is it sharp?" gets one word. A doctor who says "Tell me about it" gets the story: tight, on the stairs, two weeks, worse each morning.
- Most diagnoses come from the history. A clear structure makes sure the important parts are not missed.
The shape of a history
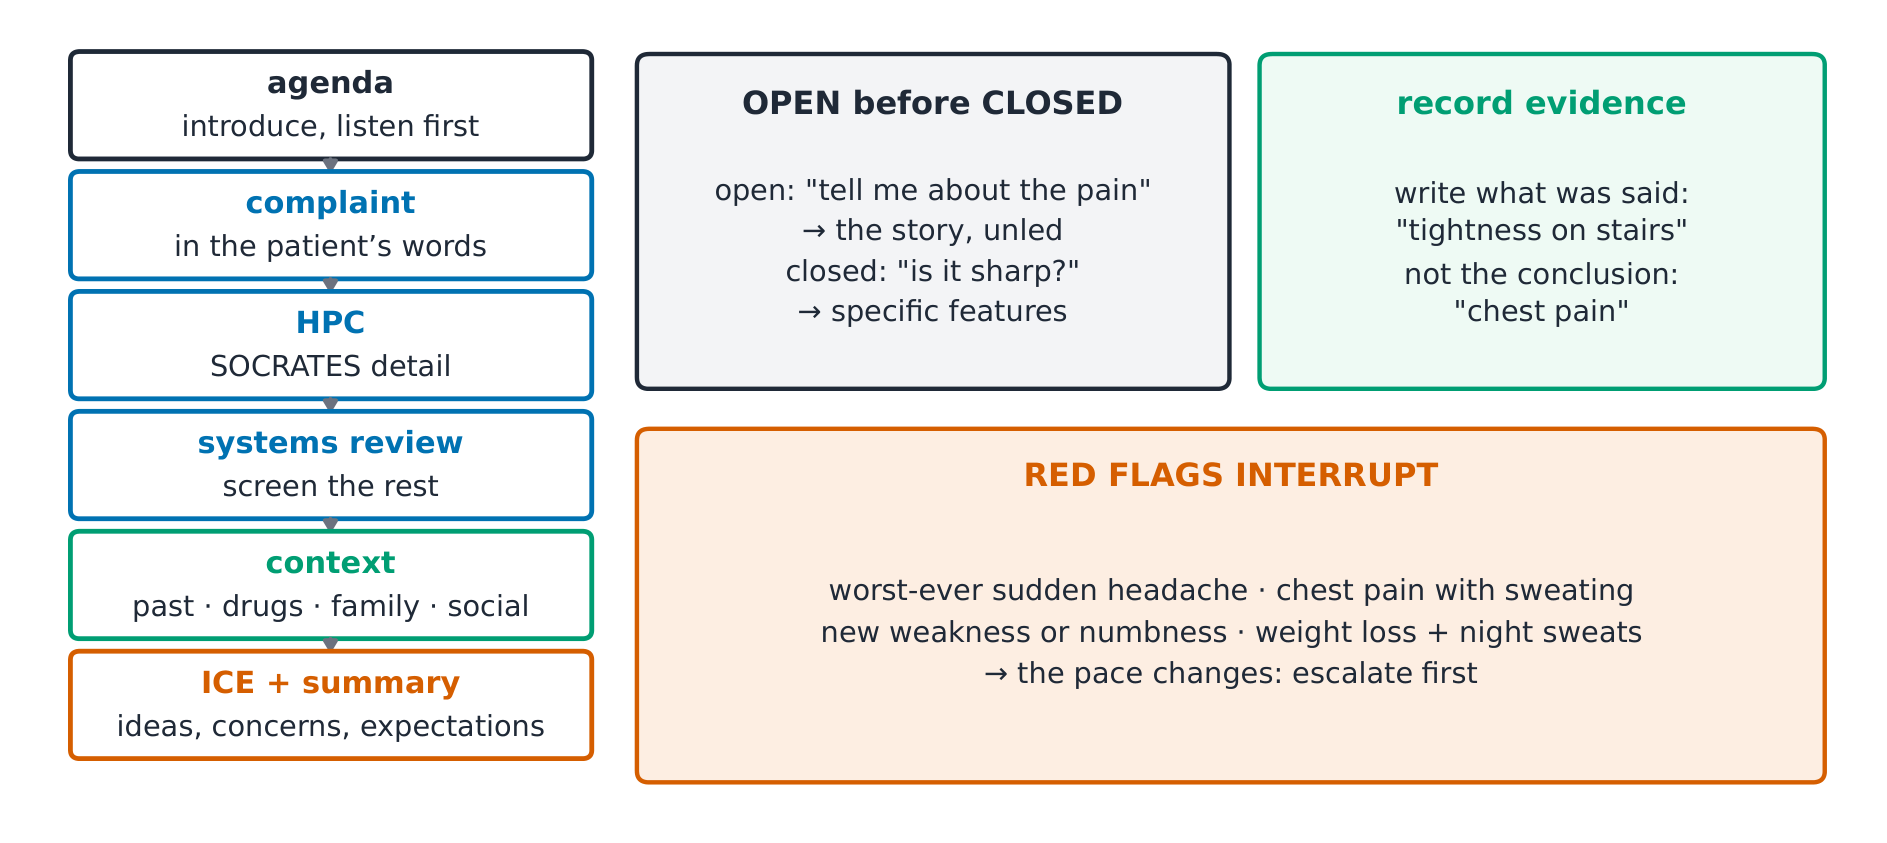
- Introduce yourself and agree the agenda. Then take the presenting complaint 主诉 in the patient's own words, and the history of presenting complaint 现病史 in detail.
- Next comes the systems review 系统回顾 (a quick screen of every body system), then past, medication, family and social history. Finish with a summary.
Put the parts of a history in order.
Độ khó 3/5 · 200 xu + phần thưởng nhỏ khi hoàn thành lần đầu tiên hôm nay
The story first, then the screen of other systems, then the background, then the patient's own view and a summary.
Open questions first, then closed
- An open question ("Tell me about the pain") lets the patient tell the story in their own order. That order, what came first and what made it worse, is itself evidence.
- Closed questions ("Is it worse lying flat?") then fill the gaps. Asking closed questions first leads the patient's answers and loses the story.
Which is the best FIRST question about a patient's headache?
Độ khó 1/5 · 100 xu + phần thưởng nhỏ khi hoàn thành lần đầu tiên hôm nay
An open question gets the story in the patient's own order; closed questions come after to fill gaps.
SOCRATES for any pain
- Site, Onset, Character, Radiation, Associations, Timing, Exacerbating and relieving factors, Severity. It is a checklist, not a script.
- Record evidence, not conclusions: write "tightness on climbing stairs", not "angina". The diagnosis comes later.
- (Fictional) "Tell me about the chest discomfort." Forty seconds of story give site (central), character (tight), timing (two weeks) and an exacerbating factor (stairs).
- Six closed questions then add radiation, associations (breathlessness, sweating), relief with rest and severity. Every SOCRATES box is filled.
Match each patient phrase to its SOCRATES heading.
Độ khó 2/5 · 140 xu + phần thưởng nhỏ khi hoàn thành lần đầu tiên hôm nay
Each phrase answers one heading; the checklist shows which headings are still empty.
"Angina" is a good way to record what the patient described in the history.
Độ khó 1/5 · 100 xu + phần thưởng nhỏ khi hoàn thành lần đầu tiên hôm nay
Record the evidence ("tightness on climbing stairs"). A diagnosis written too early hides what was actually said.
Red flags interrupt
- A red flag 危险信号 is a feature that suggests a dangerous cause: a sudden "worst ever" headache with vomiting, chest pain with sweating, a new weakness, or weight loss with night sweats.
- A red flag changes the pace at once, whatever the list of likely diagnoses says. A good history screens for red flags on purpose.
Which features are red flags that should change the pace of the consultation? Select all that apply.
Độ khó 2/5 · 140 xu + phần thưởng nhỏ khi hoàn thành lần đầu tiên hôm nay
The first three suggest a dangerous cause. A mild tension-type headache with an obvious trigger does not.
Ideas, concerns, expectations
- Ask what the patient thinks is wrong (Ideas), what worries them (Concerns) and what they hope will happen (Expectations).
- A patient afraid of cancer will not hear a reassuring plan until that fear has been named. ICE turns a plan into a shared one.
"I was hoping you could refer me for a scan today." This is the patient's —
Độ khó 1/5 · 100 xu + phần thưởng nhỏ khi hoàn thành lần đầu tiên hôm nay
It is what they hope will happen, the E of ICE. If the plan differs, it has to address this hope openly.
Common slips
- Closed questions first. They steer the answers and lose the story's sequence.
- Skipping medication and social history. Drug interactions, work and home all change risk.
- Never asking ICE. You cannot answer a fear the patient has not voiced.
Recap
- Agenda → presenting complaint → history of presenting complaint (SOCRATES) → systems review → past, drugs, family, social → ICE and summary.
- Open questions before closed; record evidence, not conclusions.
- Red flags interrupt the routine and change the pace.